


1. Context and objectives
Pudendal neuralgia (PN) is not simply “perineal pain.” It may result from, or be sustained by, several mechanisms that can combine: compression or irritation of the nerve, altered nerve mobility, protective muscle responses, and sensitization. SBNFA™ offers an integrative reading of how these mechanisms may interact with pelvic geometry, posture, the stresses of sitting, pelvic floor tension, and the pudendal nerve’s own dynamics.
In the SBNFA™ framework, when the system’s adaptive reserve is exceeded, compression, reduced nerve gliding, changes in fascial interfaces, and protective hypertonia may appear and contribute to neuropathic pain that is often poorly localized (referred pain). This complexity helps explain why a diagnostic odyssey is common, and why central sensitization may play a role in some chronic forms. Understanding these mechanisms can help guide diagnosis, avoid false leads, and support integrated care that takes posture, sitting, and rehabilitation into account.
In this context, the purpose of this knowledge base is to provide a rigorous and coherent explanatory foundation for understanding pudendal neuralgia without reducing it to an isolated symptom (“urinary burning,” “rectal pain,” “genital hypersensitivity,” etc.). It aims to clearly distinguish causes, mechanisms, and vulnerability factors, in order to move beyond a frequent clinical confusion:
- pain can be intense without any visible lesion,
- and, conversely, an anatomical abnormality can exist without pain.
In PN, where the pain is felt does not necessarily indicate where the conflict originates. Pain may be perceived at a site different from the site of nerve irritation. In some cases, symptoms felt distally within the pudendal territory may be associated with irritation located more proximally along the nerve’s course.
This knowledge base offers neither a diagnosis nor a medical protocol. It provides a mechanistic interpretive framework that any coherent care requires, and clarifies the situations in which a functional approach is relevant, versus those in which structural damage calls for a specialist evaluation.
2. Logical diagram (reading key)
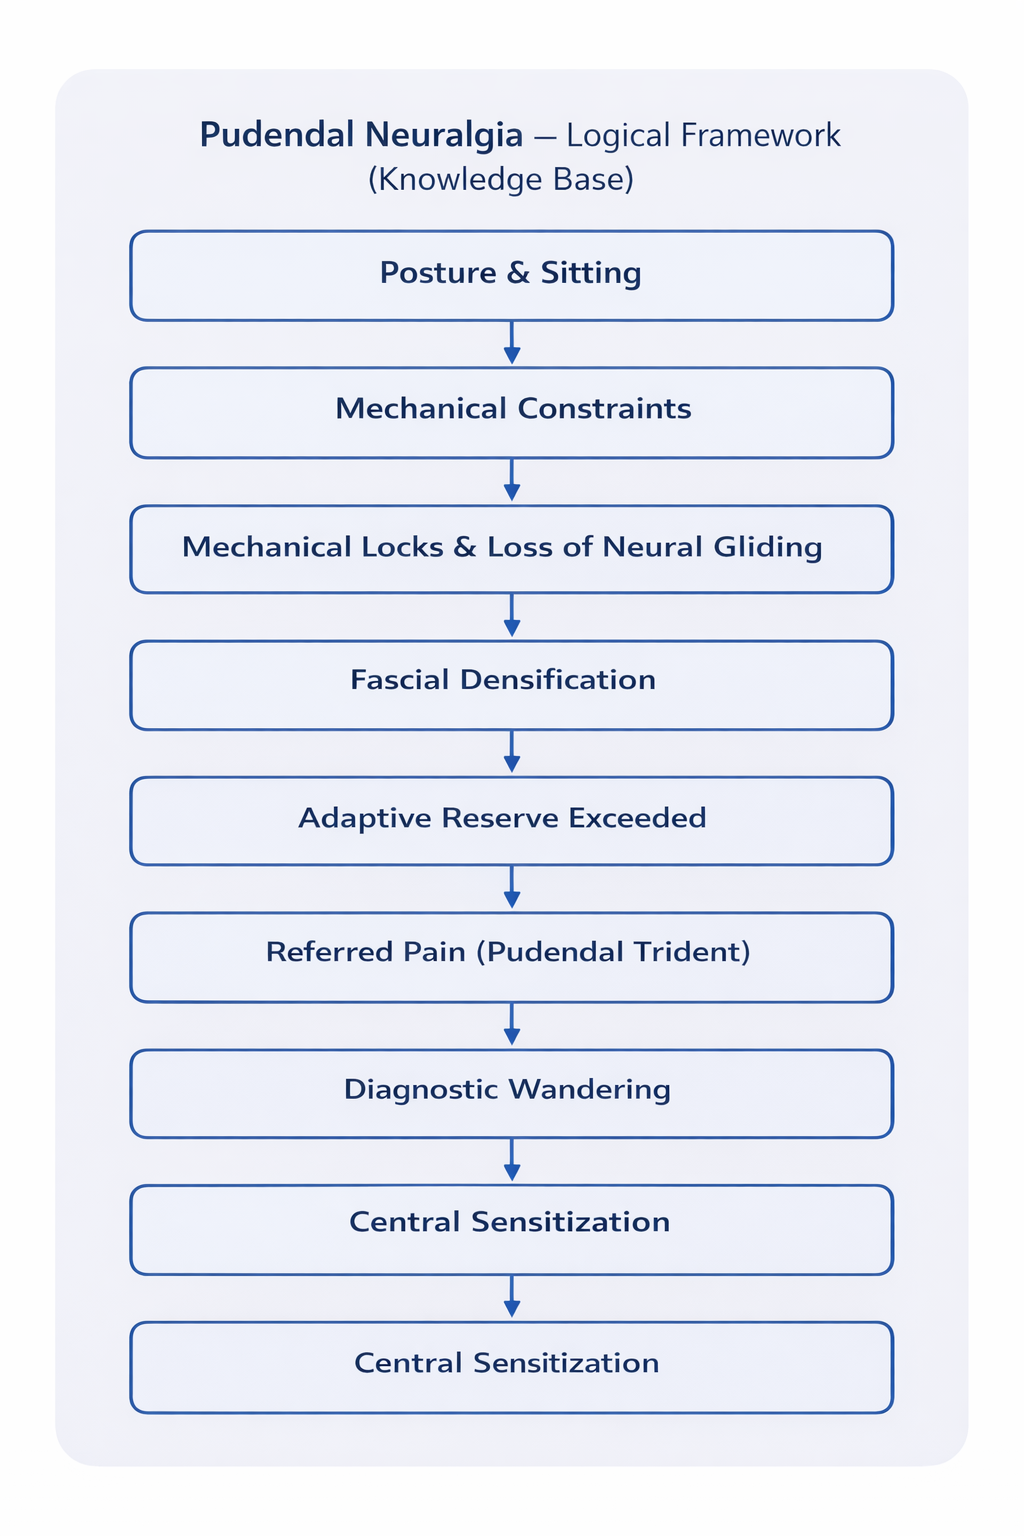
The diagram opposite offers a concise, practical reading of the mechanisms described in this knowledge base.
It represents, within the SBNFA™ framework, a chain of progressive maladaptation that may contribute to pudendal neuralgia: starting from the interaction between posture and sitting, repeated mechanical stresses can create locks and impair pudendal nerve gliding within its fascial interfaces.
Over time, the nerve’s tissue environment may become densified, which could reduce its tolerance to stress. When the system’s adaptive reserve is exceeded, neuropathic pain may appear that is often poorly localized — referred pain following the pudendal “trident.”
This mechano-neuro-fascial complexity can contribute to a diagnostic odyssey. In some chronic forms, central sensitization may set in, with the nervous system becoming hyper-reactive.
This diagram is not meant to replace reading the chapters: it serves as their compass and common thread.
3. Recommended reading path
Understanding pudendal neuralgia rests on a logical progression. Each page below is standalone, but fits into an overall line of reasoning (anatomy → locks → referred patterns → triage → tissues → chronicity).
4. Access the chapters
5. How to use this knowledge base
- Read in order for a complete understanding (anatomy → mechanics → triage → tissues → chronicity).
- Go directly to a chapter depending on your question: posture and sitting, urinary pain “without infection,” rectal pain, etc.
- Compare structural vs functional before settling on a single strategy: PN is not a single disease, but a spectrum.
- Use this knowledge base as an interpretive framework: it does not replace medical advice and does not constitute a diagnosis.
PN can combine several mechanisms (multiple locks + loss of gliding + hypertonia + sensitization). A postural improvement may be compatible with a functional or mixed mechanism, without ruling out a structural vulnerability.
6. Conclusion
Pudendal neuralgia cannot be understood through a single reading. It may result from interactions between pelvic geometry, the mechanical stresses of sitting, tissue dynamics (fascia and gliding), neuromuscular regulation (protective hypertonia) and, sometimes, central sensitization that has set in over time.
This knowledge base aims to provide robust keys to understanding: identifying zones of vulnerability, distinguishing structural from functional, understanding referred pain, and placing suffering within a coherent logic — a necessary condition for shortening the diagnostic odyssey and reconciling clinical experience with explainable mechanisms.
