


5. Why There Is No Single Treatment for Coccydynia (and How Chronicity Sets In)
Knowledge Base – Coccydynia Expert Guide
1. Why is there no single treatment for coccydynia?
(and why this is reassuring news, not discouraging news)
Generally, when pain persists, the question inevitably comes back:
“What can be done to make it stop?”
In the case of coccydynia, this question is often asked too early — or rather, asked before the problem has been properly formulated.
Coccydynia is not a disease in the strict sense.
It is a pain syndrome, that is, the final clinical expression of different mechanisms that can lead to the same symptom: pain when sitting.
Treating coccydynia as a single entity is like trying to fix a breakdown without knowing whether the problem comes from:
- a broken part,
- excessive play,
- seizing,
- or an overall imbalance of the system.
It is precisely for this reason that there is not — and cannot be — a universal treatment.
2. What the clinical literature shows
The major clinical reviews converge on one fundamental point:
the effectiveness of care depends directly on understanding the dominant mechanism.
Fogel et al. (2004) point out that treatment failures are often linked to an overly generic approach, applied without distinguishing between:
- coccydynia with a structural component,
- functional coccydynia,
- mixed forms, the most frequent in practice.
Lirette et al. (2014) stress that most people improve when the strategy is matched to the mechanism, and not when a treatment is applied in a standardized way.
In other words:
the problem is not a lack of solutions,
but a poor match between the cause and the response provided.
This diagnostic precision is all the more crucial because some persistent forms of coccydynia may involve nociplastic pain mechanisms.
Modern literature now distinguishes purely mechanical pain from pain linked to sensitization of the nervous system (Kosek et al., 2016).
Consequently, in these cases, even if the initial cause (a fall or childbirth) has disappeared, the nervous system continues to send an alarm signal. The approach must then become multidisciplinary.
For example, coccygeal hypermobility confirmed on dynamic radiographs may require local injections or stabilization, whereas pain without a structural abnormality will more likely call for pelvic floor rehabilitation aimed at relaxing the levator ani muscles (Fogel et al., 2004).
As a result, trying to treat a bony instability with relaxation, or a muscle contracture with surgery, explains most of the treatment failures observed along the care pathway (Sandrasegaram et al., 2020).
3. Why symptomatic approaches often disappoint
Faced with pain, it is tempting to try to silence it quickly: painkillers, imposed postures, rigid seats, generic advice…
These approaches can bring temporary relief, but they often fail in the medium term, because they do not change the mechanism that sustains the stress.
In mechanical coccydynia, the pain is not an isolated inflammation.
It is the signal of a system that can no longer distribute loads correctly.
- masking the alarm,
- leaving the stress intact,
- and exposing oneself to recurrence.
4. A logical hierarchy, not a recipe
Care must therefore be progressive, prioritized, and individualized.
- identify whether the problem is structural, functional, or mixed,
- identify the aggravating factors specific to the person,
- adapt the strategy accordingly.
Maigne et al. (2000) show that certain mechanical abnormalities benefit from very specific care, while others call more for restoring mobility and adaptability.
Looking for “the right treatment” without this preliminary step is like looking for a key… without knowing which door to open.
5. Why this approach changes the person’s experience
The absence of a simple answer is often experienced as abandonment. In reality, the absence of a single solution means that there are several possible levers.
Understanding this makes it possible to move beyond guilt and fatalism, and into a logic of understanding and targeted action.
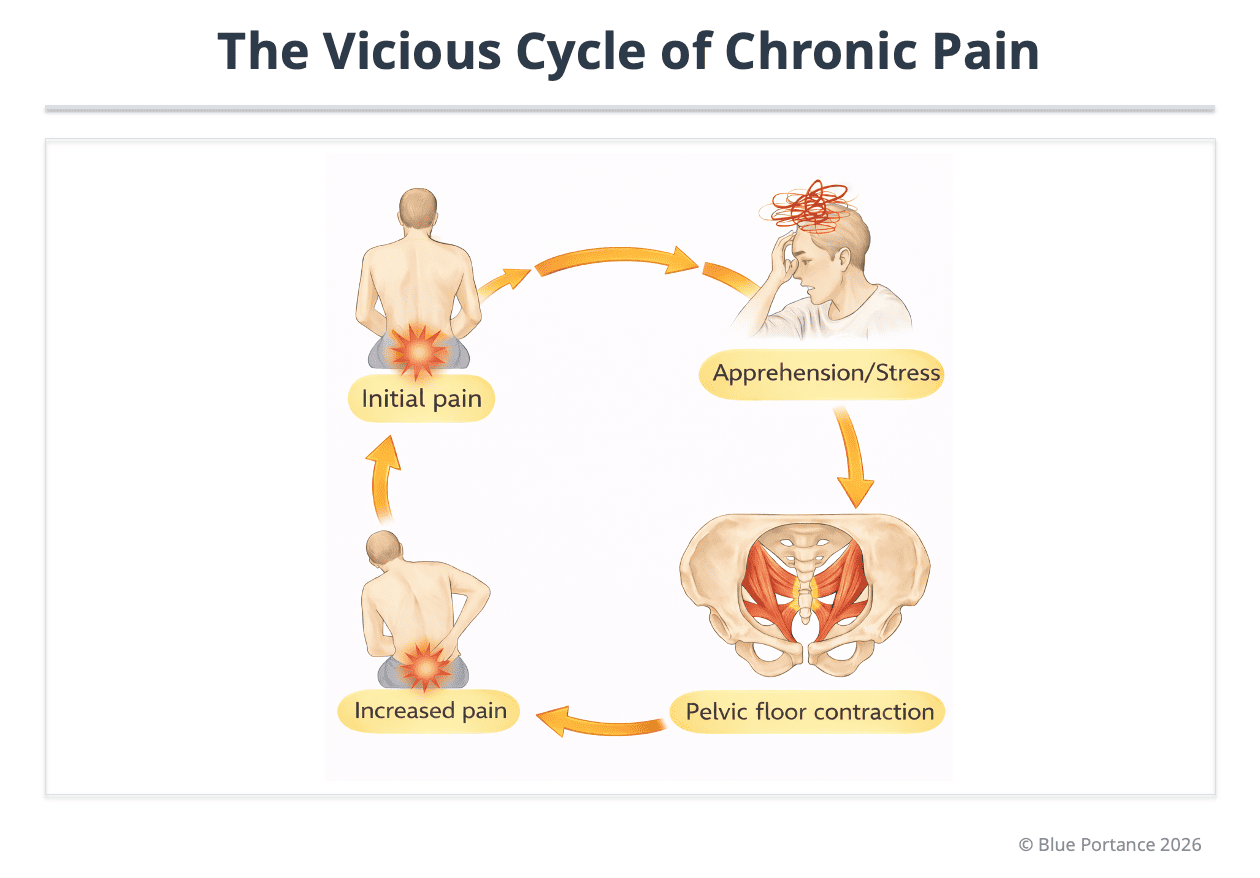
The time it takes to start appropriate care is a major prognostic factor. After several months, pain memory phenomena can set in.
The fear of pain then triggers a reflex contraction of the pelvic floor, which maintains compression of the coccyx and fuels the vicious cycle (Lirette et al., 2014).
6. What this article does… and what it does not do
First, this article does not propose a universal solution. It offers an interpretive framework.
Understanding that there is no single treatment is not an admission of powerlessness. It is recognizing that coccydynia is the outcome of different mechanisms, each requiring a response suited to its own logic.
Before trying to make the pain disappear, one must identify the mechanism that sustains it: mechanical instability, myofascial stiffening, postural maladaptation, or a process of chronicity.
This change of perspective turns the question “What should be done?” into a more fruitful one: “In this specific case, what is sustaining the stress?”
- Fogel GR, Cunningham PY, Esses SI. Coccygodynia: evaluation and management. J Am Acad Orthop Surg. 2004;12(1):49–54.
- Lirette LS et al. Coccydynia: an overview of the anatomy, etiology, and treatment of coccyx pain. Ochsner J. 2014.
- Nathan ST, Fisher BE, Roberts CS. Coccydynia: a review of pathoanatomy, aetiology, treatment and outcome. J Bone Joint Surg Br. 2010;92(12):1622–1627.
- Sandrasegaram N, Gupta R, Baloch M. Diagnosis and management of sacrococcygeal pain. BJA Educ. 2020;20(3):74–79.
- Maigne JY, Lagauche D, Doursounian L. Instability of the coccyx in coccydynia. J Bone Joint Surg Br. 2000;82(7):1038–1041.
- Kosek E, Cohen M, Baron R, et al. Do we need a third mechanistic descriptor for chronic pain states? Pain. 2016;157(7):1382–1386.
© Gil Ayache. The concepts, diagrams, terminology, and principles presented on this page constitute a work protected by copyright. They are made available to Blue Portance under an intellectual property license agreement, without transfer of economic rights or of authorship.
